
Safety & Tolerability

BRIUMVI HAS AN ESTABLISHED SAFETY PROFILE1

Safety & Tolerability
BRIUMVI HAS AN ESTABLISHED SAFETY PROFILE1
David
Living with RMS and taking BRIUMVI
People featured have been compensated by TG Therapeutics for their time.
Safety & Tolerability
BRIUMVI HAS AN ESTABLISHED SAFETY PROFILE1
David
Living with RMS and taking BRIUMVI
People featured have been compensated by TG Therapeutics for their time.
Safety & Tolerability
BRIUMVI HAS AN ESTABLISHED SAFETY PROFILE1
David
Living with RMS and taking BRIUMVI
People featured have been compensated by TG Therapeutics for their time.

IV, intravenous.
I was eager to see the BRIUMVI open-label data presented, and I would urge my peers to learn more about BRIUMVI long‑term efficacy and safety.
Derrick Robertson, MD
Individual featured has been compensated by TG Therapeutics.
I was eager to see the BRIUMVI open-label data presented, and I would urge my peers to learn more about BRIUMVI long‑term efficacy and safety.
Derrick Robertson, MD

Individual featured has been compensated by TG Therapeutics.
Adverse reactions with an incidence of at least 5% and greater than teriflunomide1
THE SAFETY PROFILE OF BRIUMVI WAS ESTABLISHED IN TWO PHASE 3 TRIALS1
Adverse reactions with an incidence of at least 5% and greater than teriflunomide1
| ADVERSE REACTIONS | BRIUMVIa (n=545) % | TERIFLUNOMIDE (n=548) % |
|---|---|---|
| Infusion reactions | 48 | 12 |
| Upper respiratory tract infectionsb | 45 | 41 |
| Lower respiratory tract infectionsc | 9 | 7 |
| Herpes virus-associated infectionsd | 6 | 5 |
| Pain in extremity | 6 | 4 |
| Insomnia | 6 | 3 |
| Fatigue | 5 | 4 |
Overall infection rates of BRIUMVI (56%) and teriflunomide (54%) were similar and infections were predominantly mild to moderate in severity and consisted primarily of respiratory tract-related infections.1,2
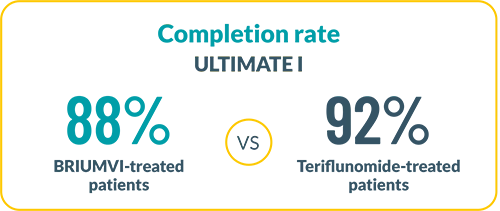
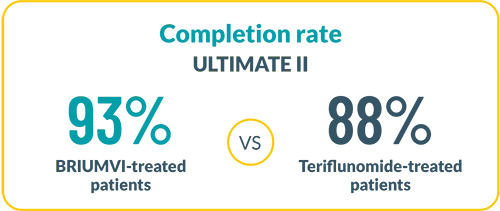
aThe first dose of BRIUMVI was given as an IV infusion of 150 mg. The second dose was given as an IV infusion of 450 mg two weeks after the first infusion.
bIncludes the following: nasopharyngitis, upper respiratory tract infection, respiratory tract infection, respiratory tract infection viral, pharyngitis, rhinitis, sinusitis, acute sinusitis, tonsillitis, laryngitis, chronic sinusitis, viral pharyngitis, viral rhinitis, viral upper respiratory tract infection, chronic tonsillitis, pharyngitis streptococcal, sinusitis bacterial, and tonsillitis bacterial.
cIncludes the following: bronchitis, pneumonia, tracheitis, tracheobronchitis, COVID-19 pneumonia, bronchitis bacterial, and pneumonia viral.
dIncludes several related terms.
<10% of patients experienced infusion reactions after Day 1 infusion3
IR rate vs dose
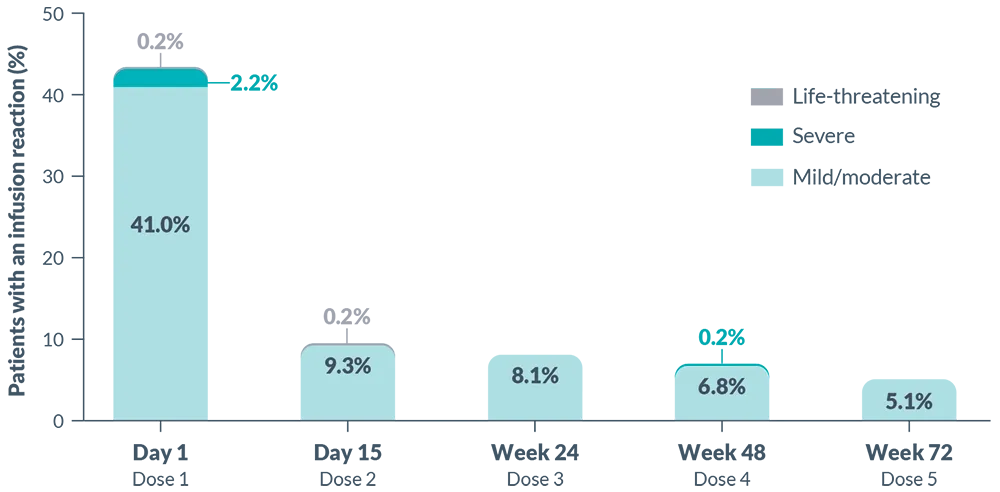
IR rate vs dose. Of the reported infusion reactions, 0.6% reactions were serious and none were fatal.1 A total of 6 patients discontinued treatment due to IRs; 5 patients experienced grade 2 IRs and 1 patient experienced a grade 4 IR.3
IR, infusion reaction.
In ULTIMATE I and II, oral acetaminophen (650 mg or equivalent) was used as an intervention for subjects who experienced fever or pyrexia after their Week 1 dose, or as clinically warranted at the discretion of the physician.3
I had tolerability issues on another infusion; those appointments regularly lasted longer than 6 hours, and it took me a day to recover. My family was worried about me. Since switching to BRIUMVI, my recent MRIs have shown positive changes in lesion size and brightness. But it’s not just about my MRIs; on BRIUMVI, I’m able to go to work before and after my infusion appointment.
Julianna, living with RMS and taking BRIUMVI.
People featured have been compensated by TG Therapeutics for their time. Individual results may vary.
I had tolerability issues on another infusion; those appointments regularly lasted longer than 6 hours, and it took me a day to recover. My family was worried about me. Since switching to BRIUMVI, my recent MRIs have shown positive changes in lesion size and brightness. But it’s not just about my MRIs; on BRIUMVI, I’m able to go to work before and after my infusion appointment.
Julianna, living with RMS and taking BRIUMVI.

People featured have been compensated by TG Therapeutics for their time. Individual results may vary.
The most common infusion reaction symptoms (>5%) were pyrexia, chills, headache, and influenza-like illness1,4
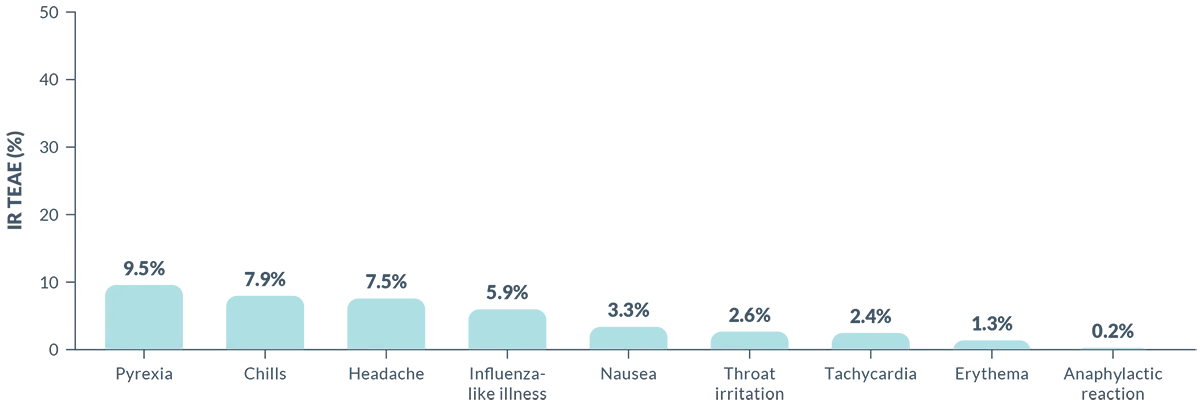
IR TEAE for BRIUMVI-treated patients in ULTIMATE I and II.
TEAE, treatment-emergent adverse event.
97% of all BRIUMVI infusions were delivered without interruption in clinical trials4
The BRIUMVI long-term safety profile is consistent with ULTIMATE I and IIa
The EAIR per 100 PY (95% CI) of any TEAE for the:
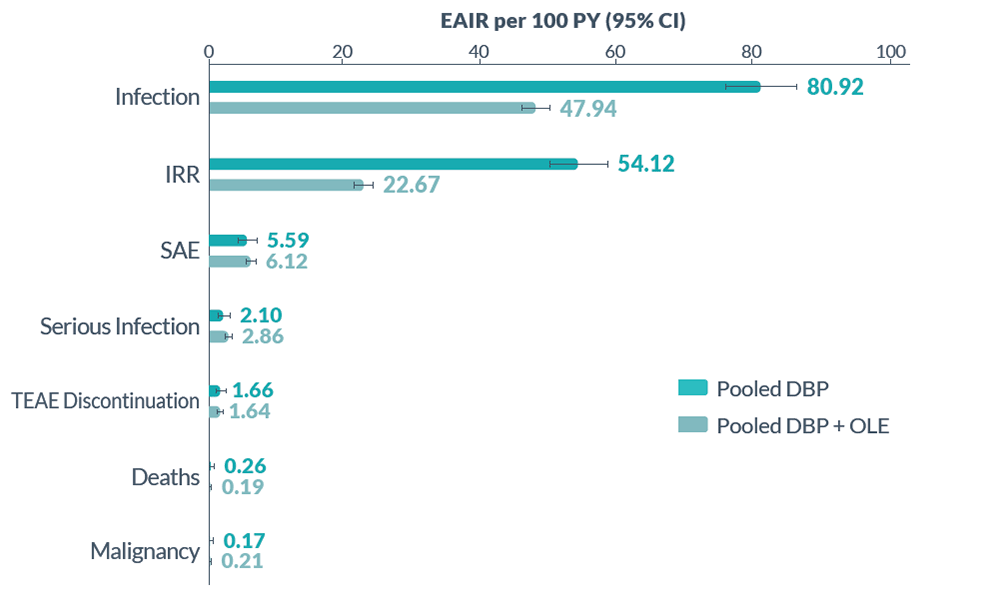
Safety summary for BRIUMVI-treated patients from the DBP and pooled DBP + OLE phases of ULTIMATE I and II. COVID events were excluded from analysis.
DBP, double-blind period; EAIR, exposure-adjusted incidence rate; IRR, infusion-related reaction; OLE, open-label extension; SAE, serious adverse event.
aData cutoff date: January 1, 2025.
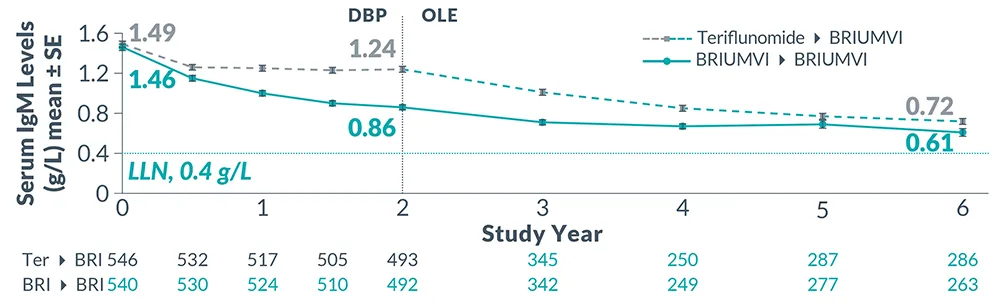
IgM levels
A
IgG levels
B
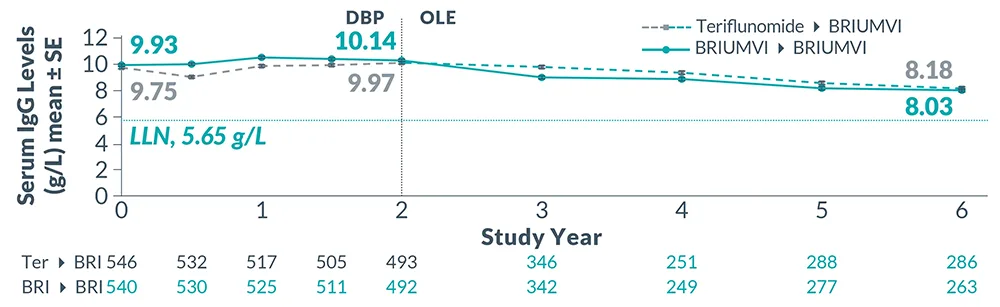
Levels of IgM (A) and IgG (B) relative to the LLN (0.4 g/L and 5.65 g/L, respectively) for BRIUMVI-treated patients from the DBP and pooled DBP + OLE phases of ULTIMATE I and II.5 As expected with any B-cell depleting therapy, decreased immunoglobulin levels were observed with BRIUMVI.1 Decrease in IgM was reported in 0.6% of patients treated with BRIUMVI compared to none of the patients treated with teriflunomide in RMS clinical trials. No decline in IgG was observed at the end of the studies.
Ig, immunoglobin;
References: 1. BRIUMVI. Prescribing information. TG Therapeutics Inc; 2026. 2. Steinman L, Fox E, Hartung H-P, et al. Ublituximab versus teriflunomide in relapsing multiple sclerosis. N Engl J Med. 2022;387(8):704-714. 3. Steinman L, Fox E, Hartung H-P, et al. Ublituximab versus teriflunomide in relapsing multiple sclerosis. N Engl J Med. 2022;387(8):704-714. Supplementary appendix. 4. Fox EJ, Steinman L, Hartung H-P, et al. Infusion-related reactions (IRRs) with ublituximab in patients with relapsing multiple sclerosis (RMS): post hoc analyses from the phase 3 ULTIMATE I and II studies. Presented at: 2022 American Academy of Neurology Annual Meeting; April 2-7, 24-26, 2022; Seattle, WA. 5. Cree BAC, Fox E, Hartung H-P, et al. Long-term efficacy and safety of ublituximab in relapsing multiple sclerosis: results from 6 years of ULTIMATE I and II open-label extension. Presented at: European Committee for Treatment and Research in Multiple Sclerosis; September 24-26, 2025; Barcelona, Spain.
